Surely more people will die from COVID than from blood clotting, due to this delay?
Or perhaps not, given that 2020 deaths in Germany were 985,145, only 4.85% higher than 2019, and only 3.2% higher than 2018 (and so basically in line with what we would expect from an aging society).
> Or perhaps not, given that 2020 deaths in Germany were 985,145, only 4.85% higher than 2019, and only 3.2% higher than 2018 (and so basically in line with what we would expect from an aging society).
Are we still having this debate.... Of course the overall mortality didn't change much, people stayed at home for literally 75% of the year.
Do you have the split stats for accidental deaths, road deaths, disease related deaths, &c. ? Because otherwise it's meaningless. We can put everyone in an artificial coma and get as little death per year as possible, it isn't a really interesting metric without the context.
You can check overall deaths for Europe on Euromomo.
It shows that despite everything we've done we've had significant more deaths in certain age groups.
You seem to be genuinely curious. For those who want to scoff it off: look at those numbers and consider the fact that these numbers are what we see after a war-sized effort to prevent more damage: in most populations only a few percent have been hit.
At the moment this epidemic runs unchecked a death rates also increase even more as it easily overwhelms even European health care if it isn't kept down.
And no, it is not just the elderly: my age group (40+) and above are all at risk.
> and consider the fact that these numbers are what we see after a war-sized effort to prevent more damage
Which doesn't seem to have worked - infection rates are dropping off all around the world, regardless of the vaccination levels. It looks more like we hit natural herd immunity at about the same time in different places whether or not masks and lockdowns were used.
The war-sized effort includes a lot of other things besides vaccines: lockdowns, masks, drastic reduction of international travel, tankerfuls of hand desinfectant, etc.
Yes, then it starts to have an impact; without those, there would have been mayhem.
If all that - which was in place in late spring and summer last year - was the reason, then why did cases start increasing anyway in the fall?
For the two additional things you've mentioned: Limiting travel works to prevent the virus from entering an area, but if it's already there and uncontrolled it wouldn't have an effect. Likewise excessive hand disinfectant doesn't seem to have had an effect, because the virus doesn't really spread through surfaces like that [0] - it was an early precaution that wasn't reexamined.
Your reasoning does not make sense at all. I hope you're just missing GP's point. Maintaining a 1 meter distance has been shown to reduce the likelihood of contagion by 80%. Using a face mask has been shown to reduce the likelihood of contagion by 40%.
With that in mind, and knowing that these were only two of the many measures made to reduce the infection rate, your parahprased statement "the measures were meaningless because they didn't stop the epidemic" is completely incorrect.
An epidemic isn't on or off. It develops at different rates, exponential->logistic if R>1 and exponentially dampening if R<1 for each area. A very steep exponential phase will obviously cause the problems we have been trying to avoid, and it's similarly obvious that the defensive measures have prevented that outcome most places.
> and it's similarly obvious that the defensive measures have prevented that outcome most places.
I'm saying that looking at aggregate outcomes and comparing locations that took these precautions to ones that didn't, this isn't obvious at all. It looks to me more like these defensive measures didn't work, and I kinda want to know why, if they're as effective as the percentages you gave.
There's plenty of null hypothesis societies to compare with. You'll find a very clear correlation between the outcomes in similar societies that used differing degrees of preventive measures.
It's hard to find a society that took no measures, as the measures so obviously work and no one wants an uncontrolled epidemic, but there's plenty of societies that had differing degrees of catastrophe up to the point where they realized this or started being serious about it. Czech Republic, Peru, Brazil, Bergamo (the latter just being unaware) +++.
Covid initially had a reproductive number between 3 and 6 in the absence of measures - higher for the latest mutations. A cumulative reduction of R of 80% + 40% would make this an R of ~0.25-0.50, but that's assuming 100% compliance everywhere and always.
Indeed, this is what you see in societies that were serious enough but didn't eradicate the virus altogether -- largely no significant epidemic, but wildfire-like eruptions of disease in local communities that don't strictly follow the measures. E.g. classrooms, public transport, homes, pubs/concerts and so on. Norway, as a case in point, currently has an R of 1.33, with measures that kept R cleanly below zero until the British mutation became dominant (through initial seeding through import and then a few almost-inevitable cases). Cities where measures can almost always be followed have almost no disease, the illness only spreads in areas where many people live close together and have children/teenagers in school. This alone is enough to threaten the capacity of intensive care.
Personally I don't really think this merits much debate anymore, if the objective is to seek the truth rather than some ulterior motive (e.g. politicians who wouldn't mind if the pension liabilities fell). It's not subtle if you actually dig into the details.
"Virus in the area" is not binary, on or off. It's always about rates and doses. Everyone is not infected instantly.
Germany provides a useful testbed for the impact of mask usage, because the mask mandates have been decided on local regional levels (federal state or city) at different times. From these different times of mask mandates and different progression of epidemic in the areas that are otherwise comparable, we can see that mask usage has a clear impact.
As said, it doesn't stop the epidemic alone, but it helps to contain it. To beat it, we need immunity through vaccines.
It did work, hospitals can only absorbs so many patients in ICU per weeks/months. Once an hospital is at 100% capacity people start dying because they can't be treated (not only for covid)
It really isn't rocket science, of course natural herd immunity is helping, spreading it over a year vs a month is a game changer though.
So COVID is dangerous enough to lock down entire societies, but not dangerous enough to justify continued vaccination when 1 in 166,666 have blood clotting? This is probably the background rate.
It seems like Europe and its bureaucrats just can't let go of lockdown. Or alternatively, they wish to push the vaccines and end of lockdown into Spring/Summer, where natural seasonality will take care of COVID and give the appearance that lockdown and vaccines were a success.
53% is nothing. Peru peaked at 260% excess mortality in February (2nd wave) and 230% in July (1st wave). My Facebook was (and is) a depressive mess of sad announcements.
> Or alternatively, they wish to push the vaccines and end of lockdown into Spring/Summer, where natural seasonality will take care of COVID and give the appearance that lockdown and vaccines were a success.
Did you somehow forget that this is the second year of Covid? We've already gone through the whole "natural seasonality" cycle and the disease is very much still here.
From an average of about 50k cases reported daily in April through October to about 200k cases reported daily in November, December, and January, then back down to 60k by March.
And there's a similar winter increase in the worldwide cases (some of which is from the US cases, but not all):
Further, South American countries were some of the worst hit during the Nov - Feb timeline. South Africa was badly hit around this time. And all these are Southern Hemisphere countries that were experiencing summer around then.
Now, there’s clear evidence that warmer weather makes things easier, since the virus has lower survivability outside a host in the heat, so all things equal, the spread would be lower in warmer weather, but it’s not so much lower that it can be considered seasonal, like the flu.
This is what seasonality means. It doesn't mean "it'll be eliminated next season".
They're referring more to, success can be claimed for lockdowns/etc whether or not they had an effect, simply by waiting until the natural seasonality causes a drop in cases.
yes, a certain seasonality is very probable. But with the variants we have right now (e.g. B1.1.7 from Kent), summer won't be enough to stem the tide. I'm saying this from a central european perspective (with not enough vaccinations either to help).
"Only" 6 5 higher mortality is huge excess mortality.
(In reality, in Sweden mortality is about 4.5 % higher than the average of 2015-2019, but that is still very significant; and of course, covid is not just that one either dies or is fine; there is the substantial but currently not very well known number of people with long-term health impact from the infection)
We already place a human value on life in healthcare, via QALY (Quality Adjusted Life Years)
This is typically about $50,000/year in places like the UK.
If you run this same calculation against what we have done for COVID, the figure comes to tens of millions of dollars per life year.
The same sums spent on lockdown and lockdown compensation could have been invested in general healthcare, or tackling air pollution (which kills 800,000 Europeans a year).
COVID lockdowns should not be immune from the cost-benefit calculations that all other Government programmes are subject to. Its also totally reasonable to ask why we tolerate influenza, which is a leading cause of deaths and fills hospitals each season, but not COVID.
> We already place a human value on life in healthcare, via QALY (Quality Adjusted Life Years)
That calculation is profoundly flawed and is based on linearity: some of the most expensive treatments are extortionate, relative to the true and actual cost to produce, against the QALY/DALY calculation. Instead, if a pharmaceutical company or a medical device company charges an extortionate amount of money for a product, the patents should be seized and governments should be allowed to produce them themselves. In a lot of cases, government funding does 80-90%+ of the research and work that allows the medical product to be marketed.
In the case of coronavirus, some governments, such as the United States, had the capability, at least theoretically to at least try and pursue the elimination strategy. That is, if the United States did not have a neoliberal government in place at the time and the citizens of the United States actually trusted its public officials. A lot of smaller countries have fared well during the pandemic. It is clear that the elimination strategy has been quite successful from an economic standpoint, for the countries that have pursued it.
> The same sums spent on lockdown and lockdown compensation could have been invested in general healthcare, or tackling air pollution (which kills 800,000 Europeans a year).
As for this matter, health insurance (private/public/national) should absolutely cover PAPRs (powered air purifying respirators) for people who are immunocompromised, have lung issues, have severe heart issues, or are at high risk from dying from illnesses like influenza. There are now half-mask (non-helmet and/or not full facemask) PAPRs that are more discreet and wearable, that are much more pragmatic than typical masks: https://industrial.optrel.com/en/product-selector-1/swiss-ai...
It is crucial that we first and foremost protect our most vulnerable, out of the principle of solidarity.
Obviously some of those deaths are directly from global warming. We have not done enough with respect to global warming, and people will die. But, this is unacceptable and we knew that it was coming. We have to do more, and putting a dollar amount on the lives of the most vulnerable is a distraction that keeps us from doing better as a society. We all pay a price by doing this.
Actually the actions work out at about $50k per qaly in US. We spent $5tn to save 1m lives Who each had about 20 years left to live. That would be $250k per qaly but hopefully not all of the $5tn was wasted/spend on additional health care costs, lot of it was to build roads and bail out mafia run multi employer pension systems in US which would have happened anyway
It's not about the "oh it's worth the risk compared to COVID 19". If it's a side effect it wasn't spotted in the trials, why was that?
It's not a side effect? It was a problem in production? What problem? Was is tampered with or was an accident? What failed in QA to let that batch come to the public? Was is a storage problem that compromised the batch quality? Was it while in transport or in the local hospital?
You talk about this like background noise. It's not. It should be investigated.
It's good that this is happening, because it shows regulators are doing their job. This is what builds trust in vaccines, not disregarding odd occurrences because they seem to have no "statistical relevance". That's just ignorance talking.
And those last couple of sentences are really, really important: If forging ahead despite the blood clotting causes folks to lose trust in vaccines, it could be worse than Covid has. And realistically, we don't need more folks to be anti-vaccine.
Exactly. This subject can easily backfire and blow the trust of a population on vaccines, or worst, on the regulators.
Imagine this is the outcome of a production problem, yet regulators refused to acknowledge this until it was out of proportions because the problem wasn't fixed. Not only people would lose trust on vaccines, they would lose trust on the regulator - this extends far beyond this vaccine, but all vaccines and medicines.
People need to feel safe, and to know that regulators are not sleeping on their job. It's not a bureaucratic job, but that they are actively looking at data and reports from doctors.
I think a lot of people (myself included) are more than willing to take a vaccine with these risks. As long as there is informed consent, what’s the problem?
Banning everyone from getting this vaccine is typical bureaucratic ass-covering. Their incentives are not aligned with ours. They get in trouble if they’re directly responsible for a few deaths, but not if they’re indirectly responsible for hundreds of thousands of deaths.
To give a point of comparison: 250 miles of driving gives you a one in a million chance of death. This vaccine is safer than that.
The problem is that it's starting to look more and more like a production problem and a bad batch, and you shouldn't be vaccinated with a product that probably should have failed QA.
It's not bureaucratic ass-covering, it's literally the protocol that's in place and has worked to keep populations safe.
>250 miles of driving gives you a one in a million chance of death. This vaccine is safer than that.
Again you're missing the point. The correct analogy would be: driving on a car that randomly combusts, or has faulty breaks, due to bad QA. And this actually happens/happened, that's why some cars are pulled from the market to be fixed when such things happen. Doesn't matter if it has happened on 1 or 2 cars, it shouldn't happen. Want another analogy?
Want another example? The Boing 737 Max.
You should only be allowed to use products that are working as expected, not faulty products. Specially not medicines and vaccines, that could blow up the trust on regulators and the vaccines.
The alternative to a car with bad brakes or a plane with design flaws is another car or another plane. The alternative to a covid vaccine is that you get covid. Even for young and healthy people, that can mean debilitating long-term illness.
There is no safe option here. We have to think like we are in war time, not peace time. Allowing people with informed consent to take this vaccine will save far more lives than banning everyone from taking it.
>The alternative to a covid vaccine is that you get covid. Even for young and healthy people, that can mean debilitating long-term illness.
Well that's arguable, I haven't had covid yet, and I don't plan on getting it. You had plenty of countries that handled covid without vaccines - we are where we are because western governments refused to take specific measures to control de pandemic (but this is another subject). So the alternative would be get a different vaccine.
Neither me EMA, or any regulator are advocating for not being vaccinated, I don't get where you're getting that from. The alternative to this vaccine is other vaccines, in EU alone 4 vaccines are approved and more are to come. Even AZ vaccine isn't excluded what so ever - they are investigating the potential cause.
>Allowing people with informed consent to take this vaccine will save far more lives than banning everyone from taking it.
Thankfully we have regulators that prevent such behavior. If there's a QA issue no one should be vaccinated with the batches affected by that, because proper QA seem to be without any of this reactions.
No one is saying side effects should not be investigated. The question is whether the vaccine administration should be halted in the meantime, and that would be determined by the risk/reward of preventing covid deaths.
Just like I trust the regulators for vaccine approval, I trust them in the decision of stopping the administration of a vaccine to further investigate the problem. This goes together.
It's not a political decision no matter how many people try to spin this. This is the outcome of doctors reporting an anomaly to a regulator. The system is working, and this should give you reassurance, not doubt about the consequences of stopping a vaccine.
I'm pretty sure they know the consequences of this setback, so for them to stop it it's because something is not right.
From the perspective of the regulators, there are asymmetric personal consequences.
If they make a decision that leads to 50 clotting deaths but saves 5000 people from COVID as a counterfactual, their head is on a chopping block because those 5000 foregone deaths are invisible but the 50 deaths are visible.
If they make a decision to halt the vaccine distribution and this kills an extra 5000 people - well that's no problem because they were just being careful.
Society has set up a political situation where there is literally only one choice that absolves the bureaucrats from a negative personal outcome. Of course they're going to go that route.
Personal incentives are incredibly powerful drivers of behavior, whatever the publicly stated reasons for an action may happen to be.
It may be the case that they've made the right decision, but we can't assume that it was for the right reasons.
You could use the same arguments and mindset when you're an antivaxx.
Vaccines can't be a holy cow that gets defended no matter what. It's always interesting that people who claim to not trust big business big pharma somehow defend everything vaccine related to death. Regulators halted it snd wait for new information to come in, that is how it's supposed to be.
Perhaps individuals should have a say as to which risk is preferable to them. As it is, the antivaxxer gets to choose not get vaccinated, but the provaxxer must wait for someone elses approval.
I'm not necessarily disagreeing with the decision, I don't know enough about the clotting data to do so, and I can certainly see the necessity in preserving the public's faith in vaccines.
I'm more saying that the incentives of regulators/politicians aren't always aligned with public health, since the decision that protects public health and the decision that protects careers aren't always the same thing.
Then it's not political reasons, it's simply self interest.
I like to believe that these institutions - regulators - know better then to cover their asses, because if that was protocol until now for sure there would be a lot of problems with medicines and vaccines.
At leas the European ones (the cases I know) seem to have been pretty competent on their jobs, so I doubt that is a motivation.
> we can't assume that it was for the right reasons
But what are “the right reasons”? This one is a moral dilemma that has no solution. “OK, let’s kill these 50 people so that that those 5000 could live.” No one in their right mind can propose that.
Overall the number of blood clots observed is actually less than expected, with an incidence lower than in the general population (i.e. without vaccine at all). My source is BBC News this evening.
On the contrary, I'm just repeating the published data and opinions of experts and indeed health agencies from the WHO to the EMA (European Medical Agency).
I think it is therefore those who are calling for who have suspended this vaccine to explain the reasons because they seem to baffle everyone.
Bearing in mind the previous 'doubts' some in the EU had about the vaccine's effectiveness for people above 65 I am not convinced that this 'cautionary approach' is all in good faith... And the head of Italy's medicine authority has just said that this was politically motivated...
What published data are you referring to? Because the event that's causing this is in no way within the statistical references most of the British media is pumping out - which is what you're talking about when you say "blood cloths".
It's not "just blood cloths", it's the type of cloths, where they are located, with low pallet count, with more incidence on a younger age group, localized in an hospital staff.
The European Union medicines regulator has reiterated there is "no indication" that the Oxford-AstraZeneca Covid jab causes blood clots, after several countries paused their rollouts.
European Medicines Agency (EMA) head Emer Cooke said she remained "firmly convinced" that the benefits of the vaccine outweighed any risks.
But even if the blood clots observed are in fact due to the vaccine the numbers are so small that it seems to me irresponsible to suspend vaccination and to publicise this so much.


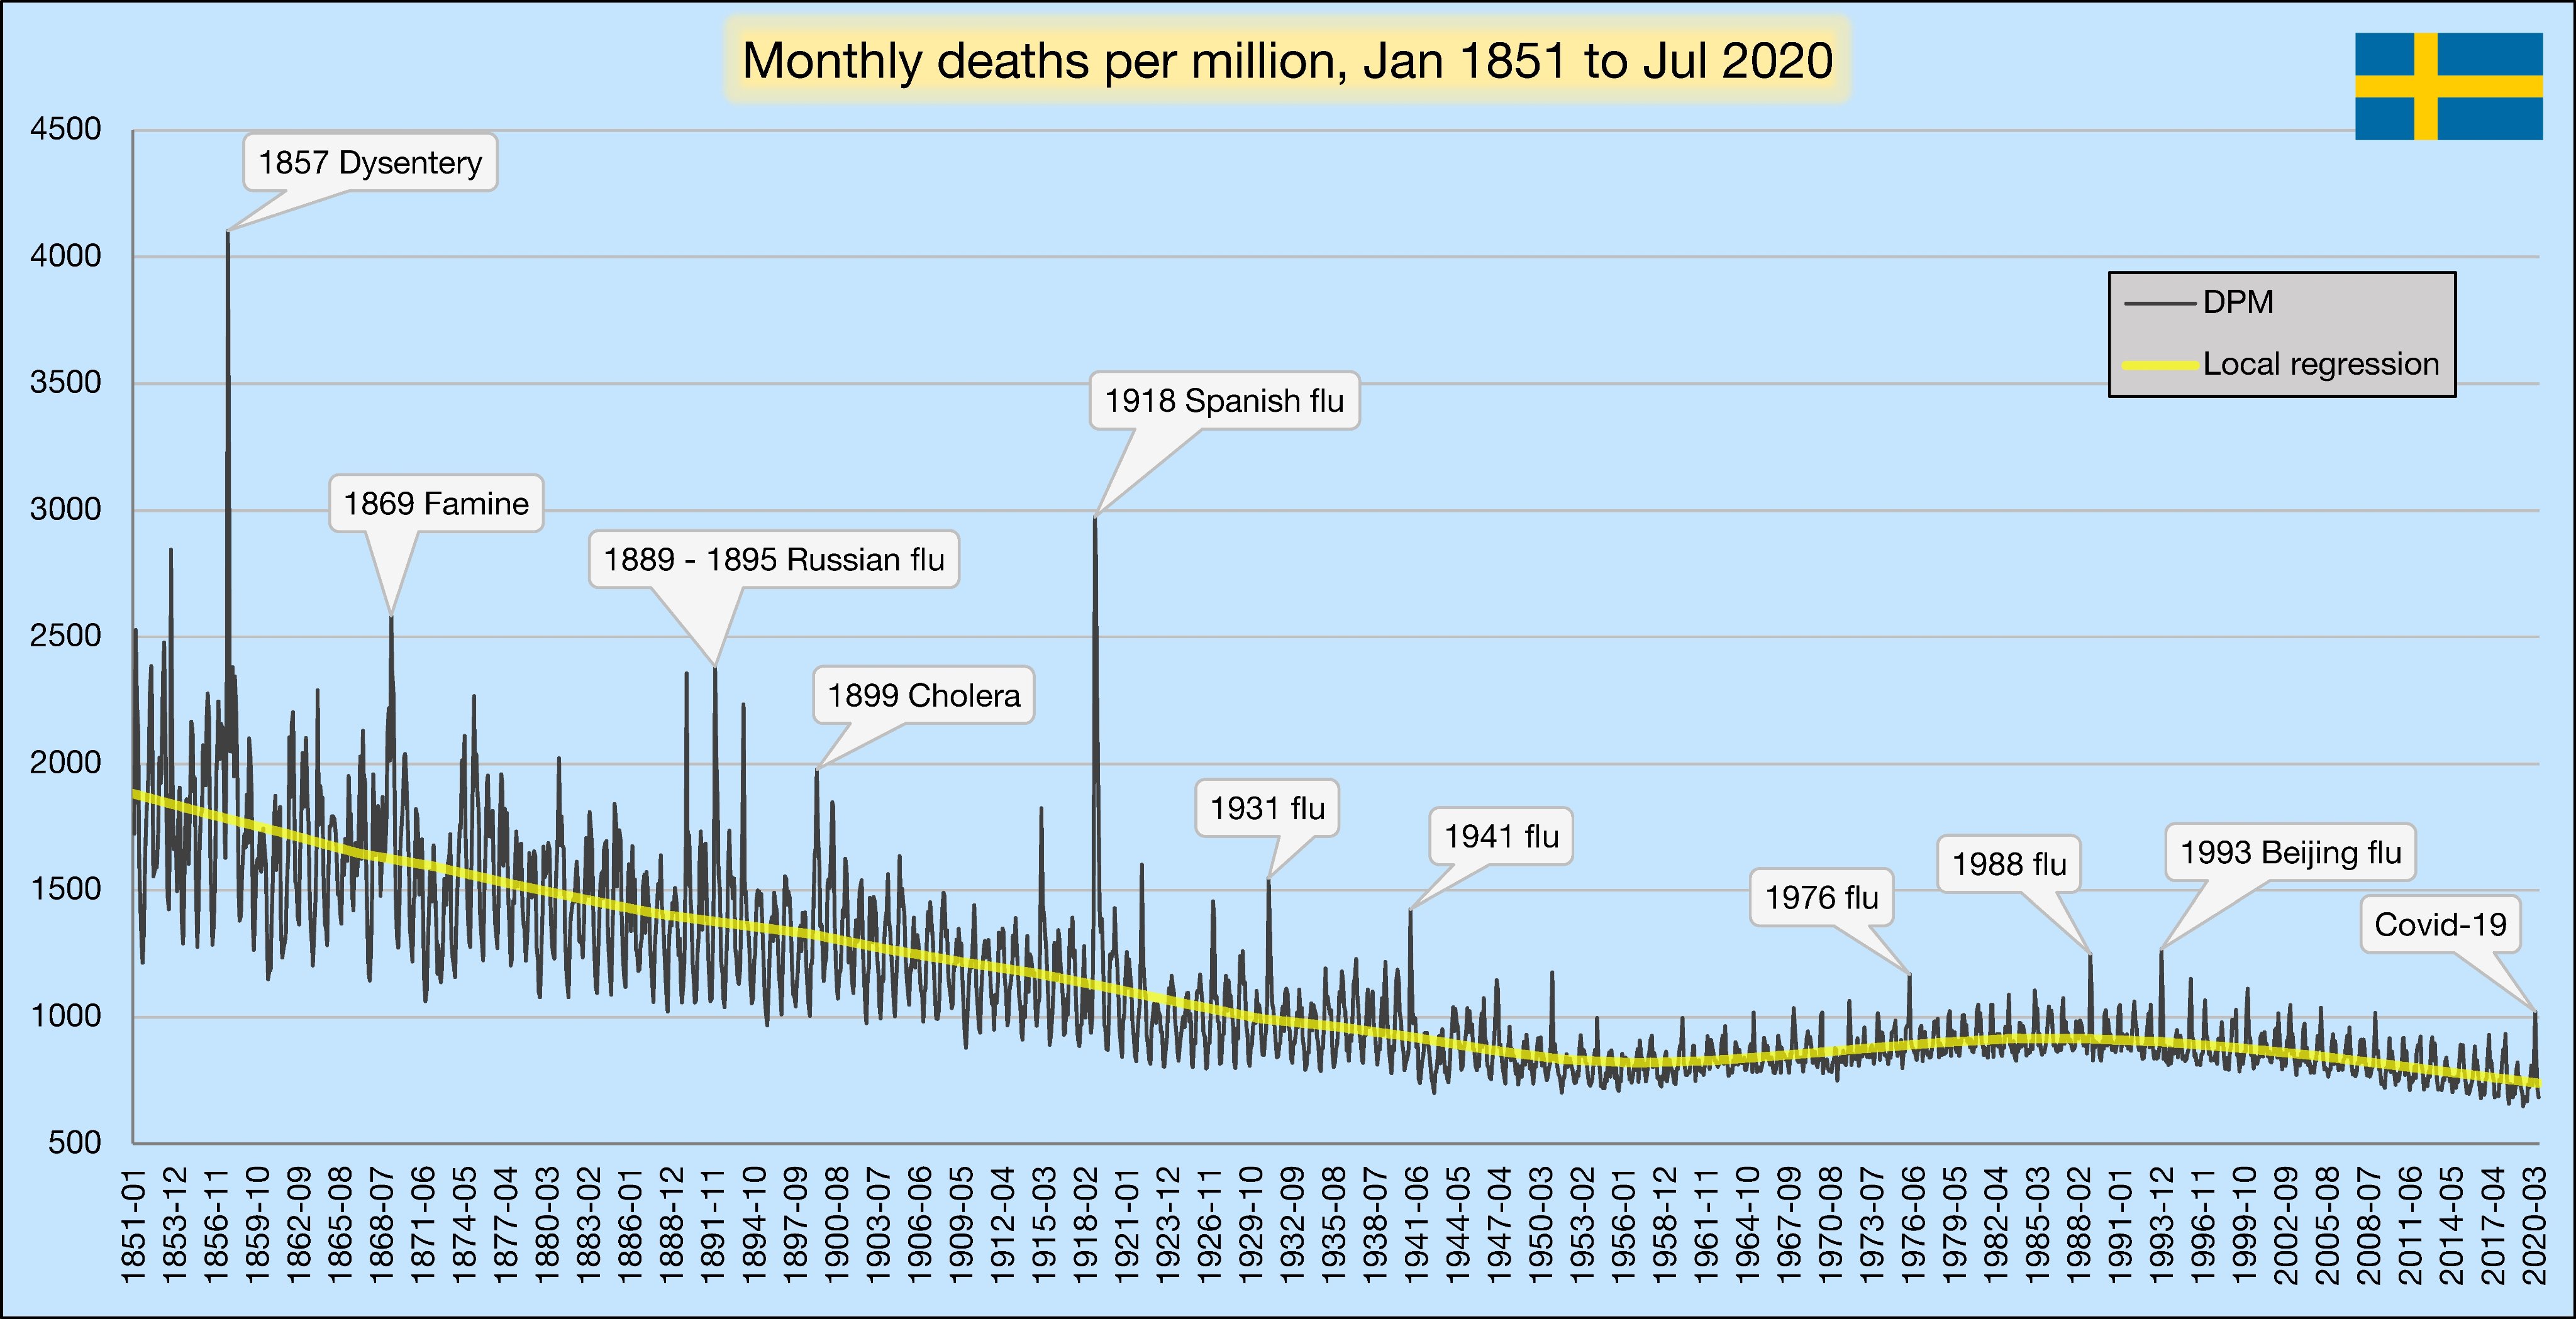
Or perhaps not, given that 2020 deaths in Germany were 985,145, only 4.85% higher than 2019, and only 3.2% higher than 2018 (and so basically in line with what we would expect from an aging society).
https://www.destatis.de/DE/Themen/Gesellschaft-Umwelt/Bevoel...